
A Targeted Approach for Patients With Refractory Shock
Dr Rawn Salenger talks about his experience with using GIAPREZA post CPB.


GIAPREZA in VASOPLEGIA
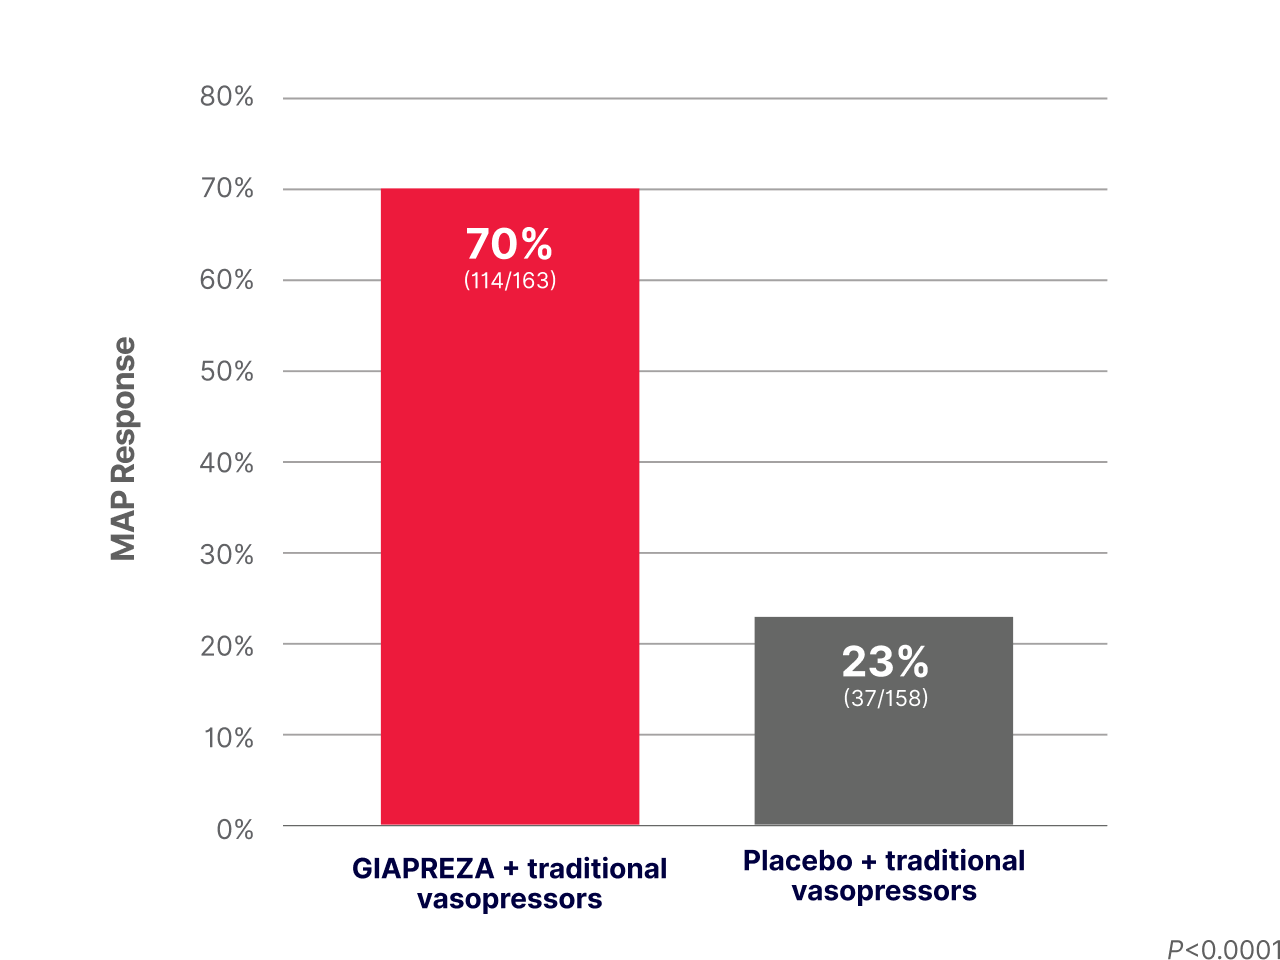
GIAPREZA was studied in ATHOS-3, an international, randomized, double-blind, placebo-controlled trial of 321 patients with vasodilatory (distributive) shock who remained hypotensive despite fluid and traditional vasopressor therapy.4,5
Slide table to view more
Treatment arms4 GIAPREZA (n=163) plus traditional vasopressors* Placebo (n=158) plus traditional vasopressors* | Primary endpoint4 An increase in MAP at hour 3 of at least 10 mmHg, or a MAP response of ≥75 mmHg, without an increase in baseline vasopressor dosing. |
Secondary endpoints4 - Mean change in cardiovascular SOFA score at hour 48 - Mean change in total SOFA score at hour 48 | |
Select additional endpoint4 All-cause mortality through day 28. |
Traditional vasopressors included norepinephrine, epinephrine, dopamine, phenylephrine, and vasopressin.5
Slide table to view more
| Select baseline patient characteristics (N=321)4 | GIAPREZA + traditional vasopressors (n=163) | Placebo + traditional vasopressors (n=158) |
|---|---|---|
| Median MAP, mmHg (IQR) | 66.3 (63.7–69.0) | 66.3 (63.0-68.3) |
| Median APACHE II score (IQR) | 27 (22-33) | 29 (22-34) |
| Cause of shock, sepsis (%) | 127 (77.9%) | 132 (83.5%) |
| Median vasopressor dose (NED), mcg/kg/min (IQR) | 0.33 (0.23-0.56) | 0.34 (0.23-0.56) |
| Vasopressin use during 6 hours before randomization (%) | 113 (69.3%) | 111 (70.3%) |
Traditional vasopressors included norepinephrine, epinephrine, dopamine, phenylephrine, and vasopressin.5
*Doses of GIAPREZA or placebo were titrated to a target MAP of ≥75 mmHg during the first 3 hours of treatment while doses of other vasopressors were maintained. From hour 3 to hour 48, GIAPREZA or placebo was titrated to maintain a MAP between 65 and 70 mmHg while reducing doses of other vasopressors.5
Slide table to view more
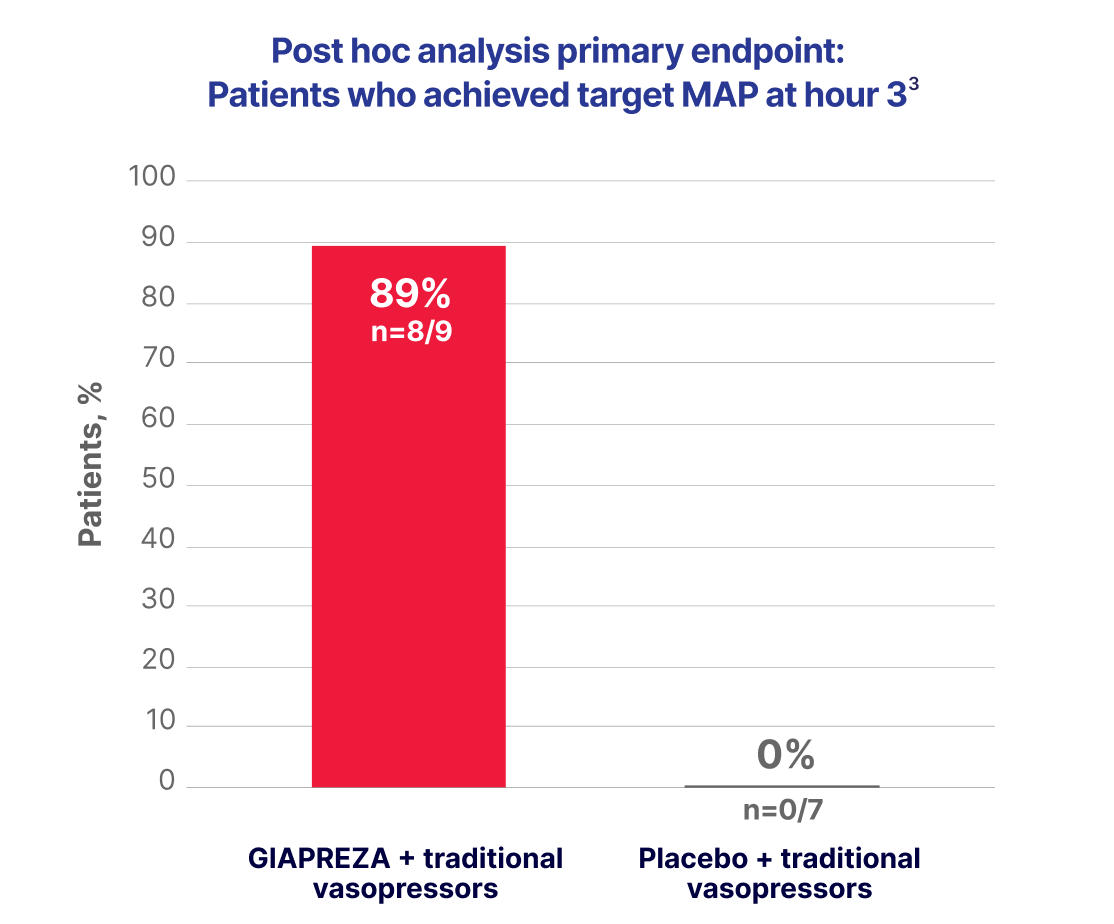
An ATHOS-3 post hoc subgroup
analysis included 16 patients who were subsequently identified as having postoperative vasoplegia; 9 patients received ANG II plus traditional vasopressors and 7 patients received placebo plus traditional vasopressors.3
Post hoc analysis primary endpoint:
Patients who achieved target MAP at hour 33
Slide table to view more
Dr Rawn Salenger talks about his experience with using GIAPREZA post CPB.

Median time to reach target MAP was 5 minutes5
In an exploratory post hoc analysis of ATHOS-3, ANG II was associated with
a greater down-titration of traditional vasopressors vs placebo3
Slide table to view more
| Characteristic | GIAPREZA + traditional vasopressors (n=9) | Placebo + traditional vasopressors (n=7) | P Value |
|---|---|---|---|
| % change in NED at hour 12 Median (IQR) | -76.5 (-87.1 to -37.5) | 7.8 (-27.6 to 17.4) | 0.0013 |
In the GIAPREZA-treated group of the overall ATHOS-3 population, patients were not necessarily on maximum doses of other vasopressors at the time of randomization. The effect of GIAPREZA when added to maximum doses of other vasopressors is unknown.5
Select clinical outcomes of the subset of study patients in the
exploratory post hoc analysis of ATHOS-37
Slide table to view more
| GIAPREZA reduced renin and ANG I levels and was associated with better outcomes7 | GIAPREZA + traditional vasopressors | Placebo + traditional vasopressors |
|---|---|---|
| Median reduction in serum renin levels, % | 54.3 | 14.1 |
| Median reduction in serum ANG I levels, % | 39.7 | 7.0 |
| Outcomes: Patients above the study population median renin (median [IQR])7 | GIAPREZA + traditional vasopressors | Placebo + traditional vasopressors |
| 28-day mortality, % [median (IQR)]* | 51 (39–65) | 70 (59–80) |
| Ventilator liberation by day 7 (alive and ventilator-free), % (median [IQR])* | 28 (18–43) | 14 (8–25) |
| RRT liberation by day 7 (alive and RRT free), % (median [IQR])* | 43 (25–66) | 12 (5–27) |
| ICU discharge by day 28, % (median [IQR])* | 44 (32–58) | 22 (14–33) |
*Values represent outcomes in patients who had renin concentrations above the study population median.7

Dr David W. Boldt presents a patient case and holds panel discussion on addressing ANG II deficiency after cardiac surgeries.
Slide table to view more
| GIAPREZA + traditional vasopressors (n=163) | Placebo + traditional vasopressors (n=158) | |
|---|---|---|
| Adverse event of any grade, % (n) | 87.1% (142) | 91.8% (145) |
| Adverse event leading to discontinuation, % (n) | 14.1% (23) | 21.5% (34) |
| Any serious adverse event with frequency ≥1% in either study group, % (n) | 60.7% (99) | 67.1% (106) |
Adverse reactions occurring in ≥4% of patients treated with GIAPREZA and ≥1.5% more often than in placebo‑treated patients included thromboembolic events, including arterial and venous thrombosis events (12.9% vs 5.1%), deep vein thrombosis (4.3% vs 0.0%), thrombocytopenia (9.8% vs 7.0%), tachycardia (8.6% vs 5.7%), fungal infection (6.1% vs 1.3%), delirium (5.5% vs 0.6%), acidosis (5.5% vs 0.6%), hyperglycemia (4.3% vs 2.5%), and peripheral ischemia (4.3% vs 2.5%).5
Use concurrent venous thromboembolism (VTE) prophylaxis.5
Fewer GIAPREZA-treated patients experienced adverse events and serious adverse events vs placebo4
Fewer GIAPREZA-treated patients discontinued treatment vs placebo due to adverse events4
Occurrence of TEAEs was comparable between the ANG II and placebo groups. There were no instances of venous or arterial thromboembolic events reported in patients with vasoplegia treated with ANG II. TEAEs from the ATHOS-3 post hoc analysis are summarized below.3
Slide table to view more
| n (%) | GIAPREZA + traditional vasopressors (n=9) | Placebo + traditional vasopressors (n=7) |
|---|---|---|
| All TEAE | 5 (55.6) | 7 (100.0) |
| Grade 3/4 TEAE | 3 (33.3) | 5 (71.4) |
| TEAE | 3 (33.3) | 5 (71.4) |
| TEAE resulting in discontinuation of study drug | 1 (11.1) | 1 (14.3) |
| Fatal outcome TEAE | 1 (11.1) | 1 (14.3) |
All patients in the angiotensin II treatment group were on anticoagulation compared to 6 (85.7%) patients in the placebo group.
Dr Rawn Salenger explains the ramifications of patients falling below a MAP of 65 mmHg post CPB.
Slide table to view more

*Instrumental ADL refers to preparing meals, shopping for groceries or clothes, using the telephone, managing money, and other such activities.9
†Self-care ADL refers to bathing, dressing and undressing, feeding self, using the toilet, and taking medications without being bedridden.9
ADL=activities of daily living; ANG=angiotensin; APACHE 2=Acute Physiology and Chronic Health Evaluation II; ATHOS-3=Angiotensin II for the Treatment of High-Output Shock; CPB=cardiopulmonary bypass; ICU=intensive care unit; IQR=interquartile range; MAP=mean arterial pressure; NED=norepinephrine-equivalent dose; RRT=renal replacement therapy; SOFA=Sequential Organ Failure Assessment; TEAE=treatment-emergent adverse event.
GIAPREZA® (angiotensin II) increases blood pressure in adults with septic or other distributive shock.
The safety of GIAPREZA was evaluated in 321 adults with septic or other distributive shock in a randomized, double-blind, placebo-controlled study, ATHOS-3. There was a higher incidence of arterial and venous thrombotic and thromboembolic events in patients who received GIAPREZA compared to placebo-treated patients in the ATHOS-3 study (13% vs. 5%). The major imbalance was in deep venous thromboses. Use concurrent venous thromboembolism (VTE) prophylaxis.
The most common adverse reactions reported in greater than 10% of GIAPREZA-treated patients were thromboembolic events. Adverse reactions occurring in ≥4% of patients treated with GIAPREZA and ≥1.5% more often than placebo-treated patients in the ATHOS-3 study were thromboembolic events (including deep vein thrombosis), thrombocytopenia, tachycardia, fungal infection, delirium, acidosis, hyperglycemia, and peripheral ischemia.
Angiotensin converting enzyme (ACE) inhibitors may increase response to GIAPREZA. Angiotensin II receptor blockers (ARBs) may reduce response to GIAPREZA.
You are encouraged to report negative side effects of prescription drugs to the FDA. To report SUSPECTED ADVERSE REACTIONS, please contact:
Before administering, please see the Full Prescribing Information for GIAPREZA.
